1. The Code Hidden in the Slide: Every Deposit Has a Causal Thread Behind It
Study illustration: The Code Hidden in the Slide: Every Deposit Has a Causal Thread Behind It
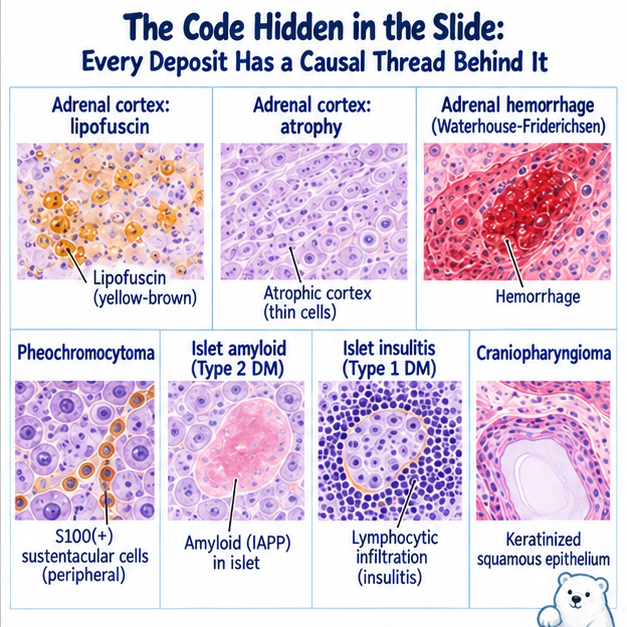
At first glance, the endocrine pathology questions on the licensing exam simply ask you to recognize a color, a deposit, a cell type on a slide, and match it to a diagnosis. But the real skill is not rote-memorizing these pairings — it is asking each clue "why does it look like this?" Once you understand that lipofuscin is a pigment accumulated over years of cellular metabolism, that amyloid is misfolded protein packed into the islets, and that insulitis is the shrapnel left behind when an immune army storms the gland, the line running from slide to diagnosis will connect itself the moment you understand it — no memorization required. The table below is not a "matching mind map" meant to be memorized up front; it is a quick-reference summary to glance back at only after you have read the whole section and thought each causal thread all the way through.
| Slide clue | Underlying cause | Points to |
|---|---|---|
| Adrenal cortical nodule + lipofuscin (yellow-brown pigment) | Pigment accumulated from years of cellular metabolism, not melanin | Micronodular hyperplasia (ACTH-independent) |
| Adrenal cortical atrophy | Exogenous cortisol suppresses ACTH; the normal cortex loses its trophic support and starves | Exogenous steroids (iatrogenic Cushing syndrome) |
| Bilateral adrenal massive hemorrhage | Severe infection associated with adrenal hemorrhage and necrosis; DIC may coexist | Waterhouse-Friderichsen syndrome |
| Chromaffin cells + S100(+) sustentacular cells | S100 stains the peripheral supporting cells, not the secretory main body | Pheochromocytoma |
| Islet amyloid (IAPP) deposition | Misfolded islet amyloid polypeptide packs the islets | Type 2 diabetes mellitus |
| Islet insulitis (lymphocytic infiltration) | An immune army storms the islets and destroys β cells | Type 1 diabetes mellitus |
| Suprasellar cystic tumor with keratinized squamous epithelium | Squamous epithelium arising from Rathke pouch remnants | Craniopharyngioma |
Swipe or scroll sideways to compare every column; keyboard: focus the table and use arrow keys.
The Adrenal Cortex: A Power Game Between "Boss" and "Sidekick"
Study illustration: The Adrenal Cortex: A Power Game Between "Boss" and "Sidekick"
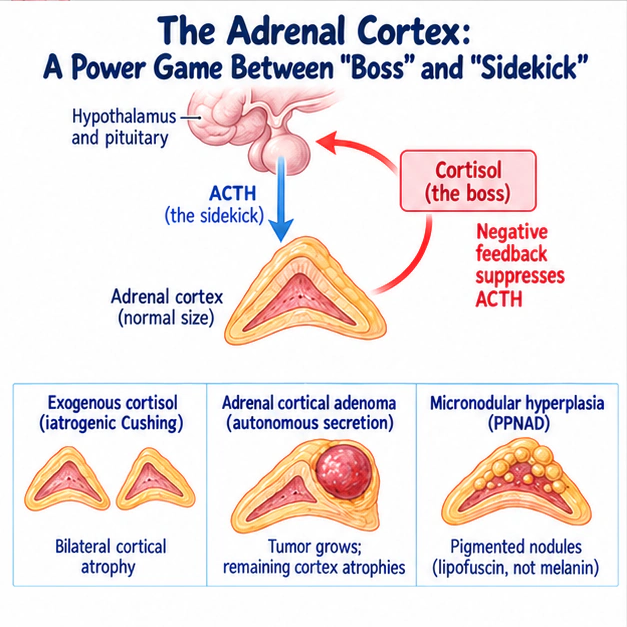
To understand every pathological change in the adrenal cortex, remember just one sentence: cortisol is the "boss," ACTH is the "sidekick."
| Disease / condition | Pathological feature | Key mechanism |
|---|---|---|
| Micronodular hyperplasia (PPNAD) | Cortical pigmented nodules, pigment is lipofuscin, not melanin | Autonomous secretion (ACTH-independent); may be associated with Carney complex |
| Exogenous (iatrogenic) hypercortisolism | Bilateral adrenal cortical atrophy | Exogenous cortisol → suppresses ACTH → cortical atrophy |
| Adrenal cortical adenoma | Unilateral, well-circumscribed, lipid-rich yellow tumor | Autonomous secretion → the tumor itself grows while the remaining ipsilateral cortex and the contralateral gland atrophy |
Swipe or scroll sideways to compare every column; keyboard: focus the table and use arrow keys.
This logic leads directly to the exam's favorite topic — sorting the causes of Cushing syndrome. The trick is to use ACTH level as the axis: the single most common cause overall is actually exogenous (iatrogenic) steroids; among endogenous causes, the most common is Cushing "disease" (a pituitary ACTH-secreting adenoma), which is ACTH-dependent (ACTH↑, bilateral hyperplasia); and among ACTH-independent causes (ACTH suppressed), the most common is adrenal cortical adenoma. As for ectopic ACTH (as in small cell lung cancer), this too is ACTH-dependent, typically with markedly elevated ACTH, hypokalemia, and skin hyperpigmentation.
Bilateral Adrenal Hemorrhage: Waterhouse-Friderichsen Syndrome
Study illustration: Bilateral Adrenal Hemorrhage: Waterhouse-Friderichsen Syndrome
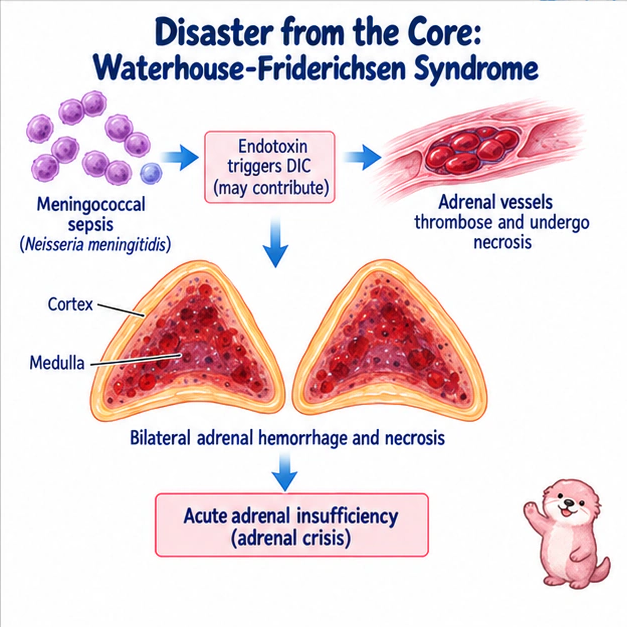
The central relationship is severe infection → bilateral adrenal hemorrhage and necrosis → possible acute adrenal insufficiency. Meningococcus is a classic cause, but other pathogens can be responsible. Coagulopathy, vascular injury and altered adrenal blood flow may contribute; DIC is not present in every case.
Do not treat a fixed medulla-to-cortex sequence as a universal diagnostic rule. Different adrenal layers may be involved. The useful learning link is between infection, hemorrhage and loss of adrenal function.
Pheochromocytoma: Don't Assign S100 to the Wrong Cell
Study illustration: Pheochromocytoma: Don't Assign S100 to the Wrong Cell
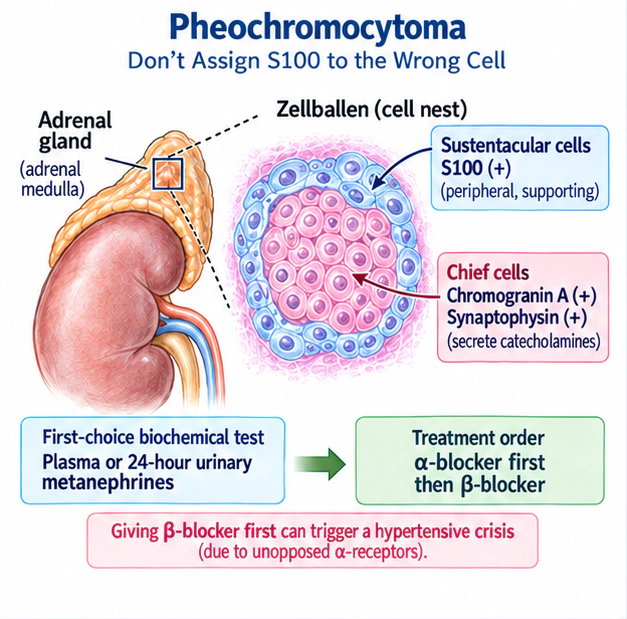
Pheochromocytoma arises from chromaffin cells of the adrenal medulla (of neural crest origin) and secretes catecholamines. Histologically the cells arrange into elegant Zellballen (cell nests) made of two cell types — and this is exactly where the exam takes aim.
| Cell | Role | Immunostaining |
|---|---|---|
| Chief cells | The main tumor body that secretes catecholamines | Chromogranin A, synaptophysin(+) |
| Sustentacular cells | Peripheral supporting cells surrounding the cell nests | S100 protein(+) |
Swipe or scroll sideways to compare every column; keyboard: focus the table and use arrow keys.
Clinically, the first-choice biochemical test is plasma or 24-hour urinary metanephrines (the highest sensitivity), not cortisol. There is an iron rule for treatment: give an α-blocker (phenoxybenzamine) before surgery, then a β-blocker. Reversing the order leaves the α-receptors unopposed and triggers a hypertensive crisis.
As for the classic "rule of 10s" (10% bilateral, 10% extra-adrenal = paraganglioma, 10% malignant, 10% in children, 10% familial), it remains a frequently tested mnemonic but is now outdated. The 2026 view: with genetic testing now widespread, roughly 30–40% turn out to be hereditary (far higher than the old 10%), linked to MEN2 (RET), VHL, NF1, SDHx; every patient is therefore recommended for genetic testing referral. Malignancy is not determined by histology but by the presence or absence of metastasis (patients with SDHB mutations carry the highest malignant risk).
Pituitary and Islets: Two Trailers
Study illustration: Pituitary and Islets: Two Trailers
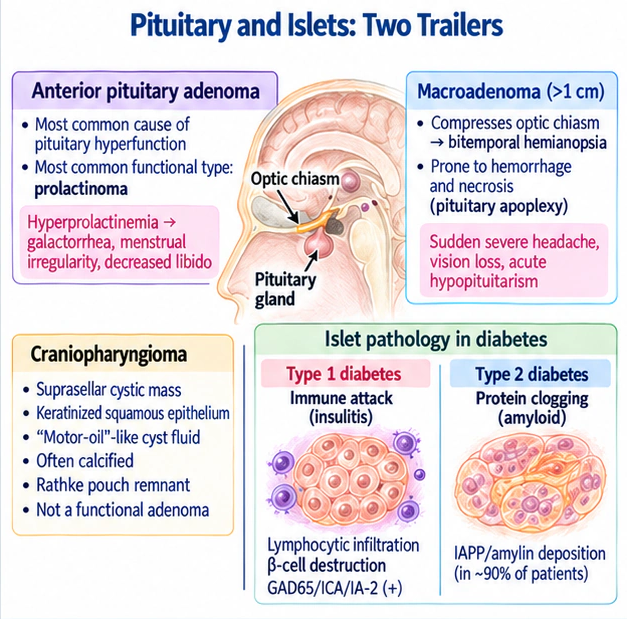
Anterior pituitary adenoma is the most common cause of pituitary hyperfunction (do not mistake this for hypothalamic disease), and among these, the most common functional type is prolactinoma (hyperprolactinemia → galactorrhea, menstrual irregularity, decreased libido). Once an adenoma exceeds 1 cm and becomes a macroadenoma, it can press upward on the optic chiasm and cause bitemporal hemianopsia, and it is prone to intratumoral hemorrhage and necrosis — this is pituitary apoplexy: sudden severe headache, vision loss, and acute hypopituitarism, a genuine endocrine emergency. Another exam favorite is craniopharyngioma: a suprasellar cystic mass containing keratinized squamous epithelium and cholesterol crystals ("motor-oil"-like cyst fluid), often calcified, arising from Rathke pouch remnants — and not a functional adenoma.
The pathology of the two types of diabetes in the islets forms a beautifully clean contrast: type 1 is the immune system "attacking" the islets (insulitis — lymphocytic infiltration, β-cell destruction, positive GAD65/ICA/IA-2 antibodies); type 2 is protein "clogging" the islets (amyloid deposition, composed of IAPP/amylin, seen in roughly 90% of patients).