The Unfinished Person: A Three-Way Conversation Among the Body, the Family, and the Developmental Clock
1. At the Triangular Table: Ethics, Consent, and a Note That Must Not Be Written
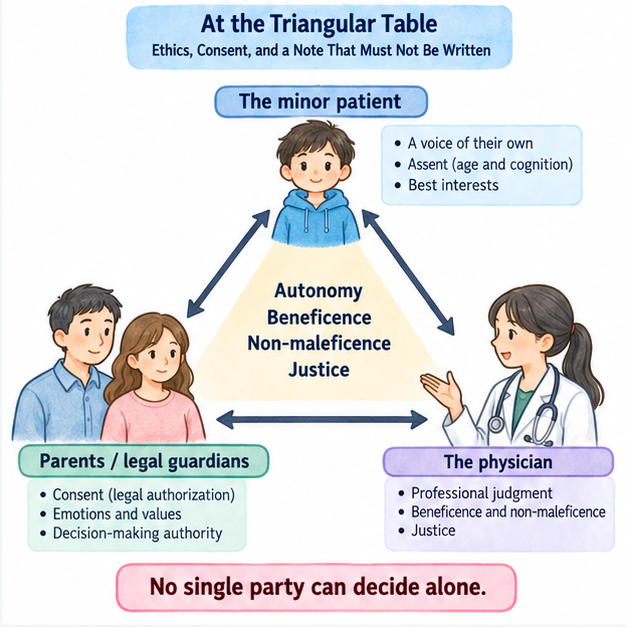
At the Triangular Table: Ethics, Consent, and a Note That Must Not Be Written
Study illustration: At the Triangular Table: Ethics, Consent, and a Note That Must Not Be Written
The root of pediatric ethics comes down to one sentence: the minor patient, the parents, and the physician form a triangular table, and no single party can decide alone. The four principles of ethics (autonomy, beneficence, non-maleficence, justice) each have their seat at this table, but the single most common wrong turn is treating "the parents consented" as equivalent to "the child also consented." Hold onto this rule and half of the ethics questions solve themselves.
Physicians Act Article 11: If You Have Not Seen the Patient, You Cannot Write "He Is Fine Right Now"
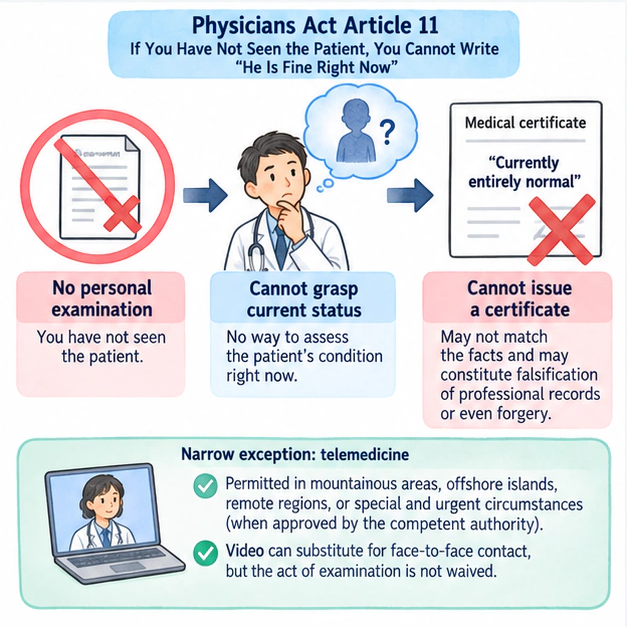
Physicians Act Article 11: If You Have Not Seen the Patient, You Cannot Write "He Is Fine Right Now"
Study illustration: Physicians Act Article 11: If You Have Not Seen the Patient, You Cannot Write "He Is Fine Right Now"
"Personal examination" is the hard threshold of medical practice. Physicians Act Article 11 states it plainly: a physician who has not personally examined a patient may not administer treatment, prescribe medication, or issue a medical certificate. Why? Because a medical certificate is a legal attestation of a patient's "current status," and without seeing the patient, there is no way to assess that status. Issuing a certificate stating "currently entirely normal" — a statement that assesses current condition — at the family's request, when the content does not match the facts, constitutes falsification of professional records or even forgery of documents.
There is only one narrow exception: mountainous areas, offshore islands, remote regions, or special and urgent circumstances, where telecommunication-based examination and prescribing are permitted once approved by the competent authority — this is the legal basis for telemedicine. Note that the exception permits substituting video for face-to-face contact; the act of examination itself is not waived.
Consent and Assent: Children Have a Voice Too
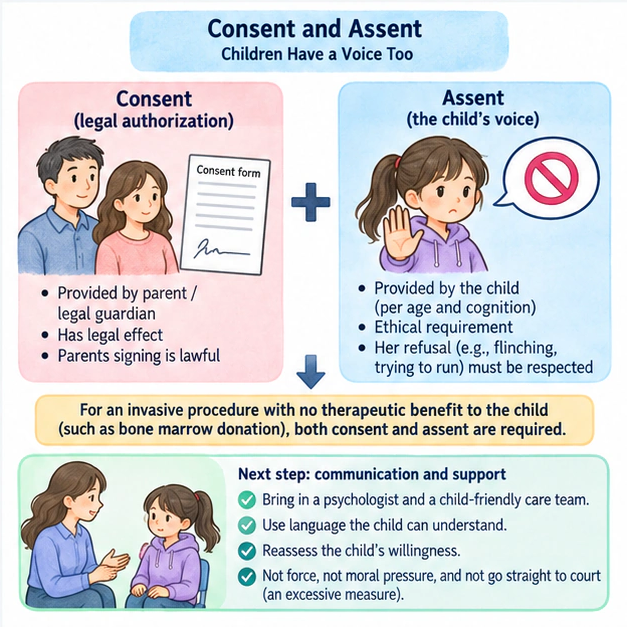
Consent and Assent: Children Have a Voice Too
Study illustration: Consent and Assent: Children Have a Voice Too
The second scenario, the older sister preparing to donate bone marrow, is the classic script for the distinction between consent and assent. One sentence captures the concept: parents provide "consent"; children provide "assent." When a procedure offers no therapeutic benefit to the child and is invasive, both are required.
Concept
Who provides it
Nature
Meaning in this scenario
Consent (legal authorization)
Parent / legal guardian
Legal effect
Parents signing for the older sister is lawful
Assent
The child (per age and cognition)
Ethical requirement
The older sister herself must also agree
↔Swipe or scroll sideways to compare every column; keyboard: focus the table and use arrow keys.
The crux of the bone marrow donation scenario is that it offers no therapeutic benefit whatsoever to the donor herself, and it is invasive (general anesthesia, bone marrow aspiration). In this kind of "for someone else, not for oneself" procedure, parental consent alone is not sufficient — every effort must be made to obtain the child's own assent. If, as the vignette describes, "the older sister flinches away and tries to run," that is not willfulness; it is her refusal expressed through behavior.
Parents can say "yes" on their child's behalf, but they cannot say "I am willing too" for the child. For an invasive procedure that offers the donor no therapeutic benefit, both voices must be heard before it counts as complete.
The correct approach is to bring in a psychologist and a child-friendly care team to communicate and reassess using language the child can understand — not moral pressure, not forcing her onto the table, and certainly not going straight to the courts, which is an excessive measure. Invoking the judicial system before the child has even been given adequate opportunity to communicate violates both the "best interests of the child" principle and the principle of "least harm."
Disclosing Prenatal Abnormalities and Peer Complaints: Give Full Information, Withhold Judgment
Disclosing Prenatal Abnormalities and Peer Complaints: Give Full Information, Withhold Judgment
Study illustration: Disclosing Prenatal Abnormalities and Peer Complaints: Give Full Information, Withhold Judgment
Once prenatal diagnosis uncovers a chromosomal or structural abnormality, the physician's role is not to choose on anyone's behalf, but to lay out the information fully and return the decision to her. Three things are non-negotiable: provide complete, objective information and prognosis; confirm the diagnosis (to avoid a false-positive misjudgment); and never actively counsel termination of the pregnancy. This last point is the one most often violated — actively urging an abortion overrides the principle of autonomy with the physician's own authority, and even if you believe it is "for her own good," you have already crossed the line.
As for the scenario of a colleague being reported — the family complains, "How did the last prenatal ultrasound miss the fetal heart defect?" — here neither extreme is acceptable. Flatly declaring a colleague negligent may harm that colleague and may not even be accurate; evading or deflecting violates honesty. There is only one correct posture: objectively explain "the inherent limitations of the examination." The sensitivity of prenatal ultrasound for fetal cardiac screening is inherently constrained by objective conditions such as fetal position, gestational age, equipment, and amniotic fluid volume — even the most thorough anatomical survey cannot achieve 100% detection. This speaks on behalf of reality, not on behalf of admitting fault or shifting blame for any physician.
2. The Rules That Save Lives: Children Collapse Only at the Very Last Moment
🔒 Members-only chapter
3. Signature Combinations and Mechanistic Chains: See These Pictures, and the Body Must React
🔒 Members-only chapter
4. The Developmental Clock: Feeding, Reflexes, and the Cadence of Puberty
🔒 Members-only chapter
5. The Invisible Chromosome: Whichever Step the Enzyme Is Missing, the Body Leaks There
🔒 Members-only chapter
6. The Memory You Inject: Teaching the Immune System to Meet the Enemy Before It Ever Arrives
🔒 Members-only chapter
7. The Injection That Got Misunderstood: Contraindications, Adverse Reactions, and the Price of a Retracted Paper
🔒 Members-only chapter
8. The Drop of Blood at Forty-Eight Hours: Screening, Health Checks, and a Trajectory Drawn on Paper